Written by Mr Juling Ong, Consultant Craniofacial and Paediatric Plastic Surgeon

Accessory auricles, also known as preauricular skin tags, ear tags or accessory tragi, are common benign congenital differences. They are usually noticed at birth as small tags of skin, often in front of the ear or along the cheek line. Some are purely soft tissue, while others contain a small central core of cartilage.

These tags are not dangerous, but many parents choose to have them removed for cosmetic reasons, to avoid later teasing, or to prevent the child from becoming self-conscious as they grow older.

One of the most important things for parents and healthcare professionals to know is that there is often an early window in infancy when accessory auricles can be removed safely and simply under local anaesthetic. If this window is missed, the child may need to wait until they are older and have the procedure under general anaesthetic.

Why timing is important

I am often contacted by parents who are disappointed to learn that their child’s accessory auricle could potentially have been removed when they were a newborn or very young baby. Unfortunately, by the time many families seek advice, their baby may already be too old for a safe and predictable procedure under local anaesthetic.

This can be frustrating and upsetting for parents, particularly when they are then advised to wait until their child is older and able to have the procedure under general anaesthetic.

In my view, early information is therefore very important. Parents should be made aware of the option of early assessment so that they can make an informed decision while local anaesthetic removal may still be possible.

Removal of accessory auricles under local anaesthetic

In practical terms, the best time to consider removal under local anaesthetic is usually from the newborn period up to approximately 3 months of age.

During this early stage, babies can often be fed, swaddled and settled comfortably enough to allow a short procedure to be carried out safely under local anaesthetic. The procedure involves removing the tag carefully, including the base and any cartilage, to reduce the chance of leaving a residual lump.

As a general guide, I would regard 3 months of age as the usual upper limit for straightforward removal under local anaesthetic.
In selected cases, it may still be possible slightly beyond this, particularly if the tag is small, narrow-based and the baby is calm.

However, this becomes much less predictable. By around 4 to 6 months, babies are usually more alert, stronger and more mobile, which can make it difficult to carry out a precise procedure safely under local anaesthetic alone.

When general anaesthetic is usually considered

If the early local anaesthetic window has been missed, or if the accessory auricle is broad-based, multiple, contains a significant cartilage core, or the child cannot safely remain still, I would usually recommend deferring removal until the procedure can be performed under general anaesthetic.

For a purely elective cosmetic procedure, this is commonly considered from around age 1, although the exact timing depends on the child, the anaesthetic team, the hospital setting, and the family’s preference.

General anaesthesia in children is very commonly used in paediatric surgical practice, but it still involves fasting, admission to hospital, recovery time and specialist anaesthetic care. Where appropriate, early removal under local anaesthetic can therefore simplify the treatment journey and avoid the need for a later general anaesthetic.

Practical guidance for parents and referrers

My general advice is as follows:

  • Accessory auricles should ideally be assessed within the first few weeks of life if removal is being considered. The earlier the referral, the better.
  • Removal under local anaesthetic is most predictable before 3 months of age.
  • After 3 months, removal under local anaesthetic becomes case-dependent and may no longer be possible.
  • If the early window is missed, removal is usually deferred until approximately 1 year of age under general anaesthetic.
  • The procedure should remove the full base of the tag, including any cartilage, to avoid leaving a residual lump.

Final thoughts

Accessory auricles are benign, and there is no medical urgency to remove them in most cases. However, if parents wish to have them removed, early referral gives them the most options.

Clear information at the newborn check, postnatal review or GP appointment can make a significant difference. It allows parents to consider a simple local anaesthetic procedure during the early months of life, rather than discovering later that this opportunity has passed.

To discuss the removal of accessory auricles further with Mr Juling Ong, book a consultation without delay.

Revision rhinoplasty is, by most measures, one of the most technically demanding procedures in facial plastic surgery. Patients who seek a second or third operation on their nose arrive with a unique set of challenges: altered anatomy, scar tissue that has changed the landscape of the nose, and often a significant emotional burden, having already been through surgery that did not deliver what they hoped for.

Understanding why revision cases are more complex and what that means for the surgeon you choose is important for anyone considering this path.

How common is revision rhinoplasty?

Rhinoplasty consistently ranks amongst the most popular cosmetic surgical procedures in the UK, and it also carries one of the highest revision rates of any aesthetic operation.

Published peer-reviewed data indicate that revision surgery is required in 5% to 15% of primary rhinoplasty cases, with a widely cited figure of 9% to 10% across large surgical series.

A study published in the Aesthetic Surgery Journal, reviewing 369 consecutive rhinoplasties, found an overall revision rate of 9.8%, with dissatisfaction occurring in 15.4% of patients – even when the surgeon considered the anatomical correction successful.

These figures are not a reflection of poor surgery alone. Rhinoplasty is an intrinsically complex operation. The nose is the most three-dimensional structure on the face; its final appearance is influenced by how the skin, cartilage, bone, and scar tissue all settle over many months, and even experienced surgeons operating to a high standard will have a proportion of patients who wish for further refinement.

What matters is how that situation is then managed – and who performs the revision.

Why do patients seek revision surgery?

The reasons patients present for revision rhinoplasty fall into two broad categories: cosmetic dissatisfaction and functional problems, though the two frequently overlap. Common concerns Mr Juling Ong sees in revision rhinoplasty consultations include:

  • Residual or worsened asymmetry of the nose or nasal tip
  • Over-resection – where too much cartilage or bone has been removed, resulting in a pinched tip, collapsed lateral walls, or a saddle nose deformity
  • Under-correction – the original concern remains largely unchanged
  • Breathing difficulties that have developed or worsened since the primary operation
  • Visible irregularities such as dorsal humps that have reappeared, or contour issues that became apparent as swelling resolved
  • Unsatisfactory nasal tip definition, projection, or rotation

It is worth noting that the final result of any rhinoplasty cannot be fully assessed for at least twelve months post-surgery, and in revision rhinoplasty cases, even longer. Swelling can mask the true outcome for a significant period, and Juling always advises patients to allow adequate healing time before considering a revision.

What makes revision surgery more complex?

The fundamental challenge of revision rhinoplasty is that the surgeon is not operating on an untouched nose. Previous surgery leaves behind scar tissue – fibrosis within the soft tissue envelope and between the skin and the underlying structural framework – that makes dissection more difficult, tissue planes less predictable, and healing less straightforward. In short, nothing behaves as it did the first time.

Where cartilage has been removed, there is often a structural support deficit that must be replaced. This is one of the defining challenges of revision work: rebuilding a nose that has been reduced requires cartilage grafts, and the primary source – the nasal septum – may have already been used or depleted during the first procedure. In these cases, cartilage must be harvested from elsewhere, most commonly the ear (auricular cartilage) or, for larger reconstructions, the rib.

Working with these graft materials demands experience and precision; the surgeon must carve, shape, and position grafts to restore both aesthetics and structural integrity, in tissue that is already scarred and less forgiving.

A peer-reviewed classification system published in the plastic surgery literature describes revision rhinoplasty as presenting ‘unexpected challenges’ even to experienced surgeons, emphasising the importance of a systematic approach to diagnosing deformities from the primary procedure before any operative plan is made. This pre-operative analytical process – assessing what has been done, what remains, and what needs to be rebuilt – is as important as the surgery itself.

The skill set a revision surgeon needs

Performing revision rhinoplasty well requires a different depth of expertise than primary surgery; not simply more of the same. Surgeons who undertake revision work regularly must have a thorough command of both open and closed rhinoplasty techniques, an understanding of the full range of grafting options and how to manage donor sites, and the ability to adapt intraoperatively when the tissue does not behave as anticipated.

Mr Juling Ong’s background in reconstructive facial surgery, including complex cases at Great Ormond Street Hospital and his wider reconstructive facial surgery practice, is directly relevant here. Reconstruction requires the surgeon to work with what is available, to think creatively about structure and support, and to anticipate how tissues will behave under tension and during healing.

These are precisely the skills that revision rhinoplasty demands. The approach to a collapsed nasal valve, a scarred tip, or a nose requiring augmentation after over-resection is fundamentally a reconstructive problem, as much as it is a cosmetic one.

Equally important is the consultation process. Patients seeking revision surgery have often had a difficult experience and may carry anxiety alongside very clear, specific concerns. Taking time to listen, to thoroughly examine the nose, to discuss what is achievable and, crucially, what is not, is an essential part of the process. Managing expectations honestly is not a limitation; it is a mark of surgical integrity.

What to look for when choosing a revision surgeon

If you are considering revision rhinoplasty, the choice of surgeon warrants careful thought, and you should consider the following when making your decision:

  • Does the surgeon have specific experience in revision rhinoplasty, not just primary procedures?
  • Do they have a reconstructive background that informs their approach to structural rebuilding?
  • Are they willing to be candid about the limitations of what surgery can achieve in your case?
  • Do they explain the surgical plan clearly, including where grafts may be sourced and why?
  • Are they a GMC-registered consultant surgeon on the Specialist Register, operating in a regulated private hospital setting?

Revision rhinoplasty is not a procedure to rush into, and it is not one to entrust to a surgeon without appropriate expertise. Allowing sufficient time for full recovery from the primary operation – typically at least twelve months, and often longer – before proceeding with any revision is essential, both to allow the tissues to settle and to give you clarity on exactly what you wish to address.

Considering revision rhinoplasty?

If you are unhappy with a previous rhinoplasty and are wondering whether revision surgery could help, Juling would be glad to see you in consultation. He will examine your nose carefully, listen to your concerns, and give you an honest assessment of what revision surgery might realistically achieve in your individual case – without pressure and without shortcuts.

May is Skin Cancer Awareness Month, and it is a timely reminder that skin cancer is now the most common cancer diagnosed in England. According to NHS data published by the British Association of Dermatologists, there were over 224,000 skin cancers recorded in England in 2019 alone – a figure that has risen by more than 26% in just six years. Behind each of these numbers is a patient facing a diagnosis, a decision about treatment, and questions about what surgery might involve and who should perform it.

As a Consultant Plastic and Reconstructive Surgeon, Mr Juling Ong sees patients at all stages of this journey. Some are referred directly by their GP or dermatologist for surgical excision. Others come having already had a diagnosis confirmed and want to understand their options for reconstruction, particularly when the lesion is on the face or hands – areas where both function and appearance matter enormously.

Here, we look at what skin surgery involves, what patients can expect and why choosing a surgeon with expertise in reconstruction and scar management makes a meaningful difference.

Understanding the most common skin cancers

The three principal types of skin cancer patients present with are basal cell carcinoma (BCC), squamous cell carcinoma (SCC), and malignant melanoma.

BCCs are the most frequently diagnosed skin cancers and typically arise on sun-exposed skin, particularly the face, scalp, and ears. Although BCCs rarely spread beyond their original site, inadequate removal can lead to local recurrence and, on the face, to significant scarring and functional disruption if not carefully planned.

SCCs are the second most common type and carry a greater risk of spreading if left untreated. A peer-reviewed UK epidemiological study published in the British Journal of Dermatology found that cutaneous SCC incidence has increased substantially across the UK between 2013 and 2018, and the condition can present on the face, lips, ears, and hands.

Malignant melanoma, though less common, is the most serious form of skin cancer. Cancer Research UK data shows that around 15,400 people are diagnosed with melanoma in the UK each year, with incidence rates having increased by more than 164% since the early 1990s. Early diagnosis and prompt surgical removal remain the cornerstone of effective treatment.

When should you see a plastic surgeon?

Not every skin lesion requires a plastic surgeon, but there are circumstances in which specialist reconstructive expertise becomes essential. You are advised seek a consultation with a plastic and reconstructive surgeon if:

  • The lesion is located on a sensitive area of the face – the nose, eyelids, lips, or ears – where standard excision alone may not achieve a satisfactory functional or cosmetic outcome
  • The tumour is large, recurrent, or has previously been incompletely removed
  • Mohs micrographic surgery has been performed, and the resulting defect requires reconstruction
  • The lesion is on the hand, where precision is critical to preserving movement and dexterity
  • You have concerns about how the scar will heal and want the best possible outcome from the outset

Early referral is always preferable. The research is clear: stage one melanoma treated promptly carries a five-year survival rate of over 95% in England, whereas advanced disease is significantly harder to treat. Please do not wait if you have noticed a changing mole, a new growth, a persistent non-healing lesion, or any area of skin that looks or feels different.

What skin surgery involves

The type of surgery required depends on the tumour’s size, location, and depth. Smaller lesions are typically removed under local anaesthetic with a margin of healthy tissue, and the wound is closed directly with sutures. The tissue is then sent for histological analysis to confirm that the margins are clear.

Larger or more complex tumours may require reconstruction after excision. This could involve a local skin flap – where nearby tissue is rearranged to cover the defect – or a skin graft, where tissue is taken from another part of the body. When Mohs surgery has been used to remove the cancer layer by layer (a technique that is particularly valuable for facial lesions, as it minimises unnecessary tissue removal), Mr Juling Ong will often then provide the reconstruction once the Mohs surgeon has confirmed clear margins. General anaesthetic may be required for more extensive procedures.

Why surgical technique and scar management matter

Skin surgery always leaves a scar; this is unavoidable and is discussed with every patient during their consultation. However, the quality of the scar is not simply a matter of chance; it is directly influenced by surgical technique, tissue handling, suture placement, and aftercare.

On the face and hands, getting this right from the very first operation is critically important. Incisions planned along natural skin tension lines and the contours of the face heal far more discreetly than those that cut across them.

The choice of suture material, the layered closure technique, and the tension applied to the wound edges all influence the result. Juling’s training as a reconstructive surgeon, including his work at Great Ormond Street Hospital managing complex paediatric cases, underpins this approach to precision and attention to detail in every skin surgery procedure.

Following surgery, scar management may include silicone-based products, sun protection, and, in some cases, further scar treatment procedures. Juling works closely with each patient to monitor healing and offer guidance at every stage.

Complementing reconstructive facial surgery

Juling’s skin surgery work sits alongside a broader specialism in reconstructive facial surgery. For patients who require more extensive reconstruction following tumour removal – for example, where a significant portion of the nose, eyelid, or lip is affected – the same reconstructive principles that inform his facial work apply directly.

The goal is always to restore both function and form, preserving the integrity of the face in a way that reflects both the complexity of the surgery and the patient’s quality of life afterwards.

Concerned about a lesion? Please do not delay

If you have noticed a skin change that concerns you, or if you have already been advised that surgical removal is recommended, Mr Juling Ong would be glad to see you for a consultation. He practices at leading private hospitals in London and provides a thorough assessment of your lesion, a clear explanation of your surgical options, and an honest discussion of what you can expect from treatment and recovery.

Skin cancer is highly treatable when caught early. This Skin Cancer Awareness Month, please take any skin changes seriously and seek an expert opinion without delay.

If you have been considering cheek or jaw augmentation, you may have come across two surgical options: facial implants and facial fat grafting. Both are well-established procedures that can address volume loss, reshape facial contours, and restore a more youthful or defined appearance.

The best approach depends on the individual – what they hope to achieve, their anatomy, and the amount of change they seek.

Here we explore both options in detail, comparing their longevity, recovery, candidacy and the quality of results they can produce.

Understanding the two approaches

Facial fat grafting involves harvesting a small amount of fat from a donor site on your own body – typically the abdomen, flanks, or inner thighs – purifying it and injecting it into the areas of the face where volume is needed.

It is a minimally invasive procedure that uses your own biological tissue, making rejection impossible. Because the fat is autologous, which means from your own body, it integrates naturally with surrounding tissues and can also have regenerative benefits, with published research suggesting that adipose-derived stem cells within the graft contribute to improvements in skin quality.

Facial implants, by contrast, use pre-formed or custom-made biocompatible materials – most commonly medical-grade silicone or porous polyethylene – to augment the underlying bony architecture of the face. They are fixed to bone using small titanium screws and are placed via discreet incisions, usually inside the mouth, leaving no external scarring. Implants are most commonly used for cheek and jaw augmentation, and can produce immediate, precise and permanent structural changes.

Longevity: what does the evidence say?

Longevity is one of the most frequently discussed differences between these two procedures. Facial implants offer a truly permanent result: once in position and healed, they remain stable for life and do not change with normal ageing or weight fluctuation. This predictability is a genuine advantage for patients seeking structural definition that will last indefinitely.

Fat grafting is often described as semi-permanent, but this requires some nuance. Not all the transferred fat survives the initial graft – a proportion is reabsorbed in the weeks following surgery as the new blood supply is established.

Published research in Plastic and Reconstructive Surgery established that fat, which successfully integrates with surrounding tissue, behaves as a permanent addition.

However, a systematic review published in the Journal of Plastic, Reconstructive and Aesthetic Surgery found that retained graft volume varies considerably, and patients should be counselled that a secondary fat grafting session may be needed to achieve the desired result. A useful rule of thumb is to expect that around one-third of the grafted fat may not survive, though this figure varies significantly depending on technique and individual physiology.

It is also worth noting that fat, unlike an implant, will continue to age naturally alongside the rest of your face. Many patients find this a positive quality, as the result evolves gradually rather than remaining fixed as surrounding tissues change over time.

Recovery after facial sculpting surgery

Both procedures are typically performed as day cases, and most patients return to work within a few days. That said, there are some differences in what to expect.

With facial fat grafting, bruising and swelling are common in both the donor and recipient areas and generally settle within one to three weeks. There is often a period of apparent over-correction immediately after surgery, as the face can look fuller than the final result. This resolves as the non-viable fat is reabsorbed over several weeks. Final results typically become apparent at around three months. One advantage of fat grafting is that the procedure involves no foreign material; there is no risk of implant-related complications.

Facial implant surgery has a comparable recovery timeline, with swelling subsiding over 2 to 6 weeks. Results are immediately visible and highly consistent. There is a small risk of infection in the early post-operative period, which is managed with a short course of antibiotics.

A 2023 comparative study examining malar augmentation found that patient satisfaction was high across both implant and fat grafting groups, with the implant cohort reporting marginally higher satisfaction and a low but slightly elevated complication rate.

Candidacy: which approach suits which patient?

The right choice depends on several clinical factors.

Facial implants are particularly well-suited to patients who require significant structural augmentation, such as a recessed chin, flat cheekbones with minimal soft tissue, or facial asymmetry linked to underlying bony deficiency.

Fat grafting is often the preferred approach for patients whose primary concern is age-related volume loss rather than structural deficiency; those who have lost the soft-tissue fullness that characterises a youthful face, particularly in the cheeks, midface, and jawline.

Because fat can be placed in precise small aliquots across multiple compartments simultaneously, it is well-suited to patients seeking an overall softening and volumisation rather than a single focal change. Fat grafting to the cheeks typically produces a softer improvement in malar contour than implants, with the additional benefit of correcting subtle asymmetries across multiple facial zones in a single session.

Achieving natural-looking results

When performed by an experienced surgeon, both techniques can produce highly natural outcomes. With fat grafting, the softness of the result is often cited as a key advantage as it integrates seamlessly with surrounding tissues and moves naturally with the face. There is no palpable foreign body, and the gradual nature of the final result can make the change appear to others as though you simply look well-rested or refreshed. The regenerative properties of the graft may also improve skin texture and quality in the treated area over time.

Facial implants, when appropriately sized and correctly positioned, can also look entirely natural. The key is careful pre-operative planning: selecting the right implant profile, volume, and placement to complement the patient’s existing facial structure rather than imposing a change that looks incongruous. In skilled hands, cheek implants can restore the high malar projection associated with youth while simultaneously reducing the appearance of under-eye hollowing and nasolabial folds.

In some cases, combining both techniques produces the most balanced result, for example, using an implant to restore structural projection and fat grafting to soften the transitions and add overall fullness.

Making the right decision for you

The decision should be guided by your anatomy, your aesthetic goals, your tolerance for the respective recovery processes, and your preference for a natural versus a more defined structural outcome.

If you are considering either procedure, the next step is to arrange a consultation so we can discuss your concerns in detail, assess your facial anatomy, and explore which approach – or combination of approaches – is most likely to achieve the outcome you are looking for. Mr Juling Ong offers both facial implants and facial fat grafting and will always recommend what he believes to be most appropriate for you as an individual.

To arrange a consultation with Mr Juling Ong, please call 020 7927 6528 or email info@julingong.com.

Blepharoplasty, or eyelid surgery, is one of the most effective procedures for rejuvenating the eye area. In its cosmetic form, it can refresh the eyes and create a brighter, more rested appearance without changing the natural character of the face. However, blepharoplasty is not always performed solely for aesthetic reasons. In some patients, eyelid surgery is undertaken for a functional purpose – most commonly to improve vision or restore the normal support and position of the eyelids.

Functional blepharoplasty

Functional blepharoplasty is most commonly performed on the upper eyelids, where excess skin or drooping tissue can hang over the lash line and begin to interfere with the upper field of vision. This may develop as part of the natural ageing process, or it may be related to inherited anatomy, brow descent, or eyelid weakness.

In these cases, the aim of surgery is not simply to make the eyelids look better, but to restore a clearer visual field, reduce heaviness, and improve eyelid function. Many patients also notice that their eyes feel less tired once the excess weight of the upper lid has been relieved.

Functional concerns can also affect the lower eyelid, although this is less often described as a ‘functional blepharoplasty’ in the traditional sense. Some patients develop lower lid laxity, malposition, or retraction, which may lead to eye irritation, watering, dryness, or an unnatural appearance. In these situations, surgery may involve lower eyelid reconstruction or support procedures, designed not only to improve appearance but also to restore proper eyelid position and protect the eye’s surface.

How do I know if I’m a candidate for functional blepharoplasty?

Mr Juling Ong can assess whether functional eyelid surgery is appropriate by carefully examining the eyelids, brow position, skin excess, and eyelid support. In the case of the upper lids, this is often combined with a visual field assessment to determine whether the eyelid tissue is significantly obstructing vision.

For the lower lids, assessment focuses on eyelid tone, position, support, and the relationship between the lower lid and the eyeball. This helps determine whether a patient would benefit from reconstructive lower lid tightening, repositioning, or support, often in combination with cosmetic refinement.

Cosmetic blepharoplasty

Cosmetic blepharoplasty is performed when a patient wishes to improve the appearance of the eye area and achieve a more youthful, rested, and refreshed look. It may be performed on the upper eyelids, the lower eyelids, or both together.

Aesthetic improvement of the upper lid

Upper eyelid blepharoplasty treats the area between the lash line and the brow. It is commonly used to address:

  • heavy or hooded upper eyelids
  • loose or crepey skin
  • a tired or aged appearance
  • loss of definition in the upper eyelid crease
  • bulging of the fat pads

The goal is to create a smoother, lighter upper eyelid contour while preserving a natural appearance.

Upper blepharoplasty surgery results

Aesthetic improvement of the lower lid

Lower eyelid blepharoplasty focuses on the area beneath the eye and is used to treat:

  • puffiness or eye bags
  • excess lower eyelid skin
  • wrinkles or crepiness
  • hollowing of the tear trough or an uneven lid–cheek junction

Modern lower eyelid surgery is not simply about removing tissue. It is often about repositioning fat, preserving volume, and reconstructing lower lid support to create a smoother, more elegant transition from the eyelid to the cheek. In the right patient, this produces a result that looks fresher and more refined, while avoiding an over-operated or hollow appearance.

Does the procedure differ between cosmetic and functional blepharoplasty?

The basic surgical principles overlap, but the emphasis differs depending on whether the priority is function, aesthetics, or both.

For an upper blepharoplasty, Mr Ong places the incision within the natural eyelid crease so that the scar heals discreetly. Excess skin is removed, and where appropriate, underlying muscle or protruding fat may also be adjusted. In functional cases, the priority is to remove the tissue obstructing vision while maintaining a natural contour. In cosmetic cases, the focus is on restoring a more youthful and refreshed appearance without making the eyes look unnatural or overly hollow.

For a lower blepharoplasty, the approach depends on the patient’s anatomy. An incision may be placed just beneath the lash line, or in selected patients, on the inside of the lower eyelid using a transconjunctival approach. Some patients benefit from both a transconjunctival approach as well as a small resection of skin below the lash line. Younger patients with prominent eye bags but good skin tone may not need skin removal at all, and may benefit from internal fat repositioning or reduction alone.

Importantly, lower eyelid surgery often requires attention to structural support and reconstruction as well as aesthetic improvement.

If the lower lid is lax or at risk of pulling downwards, supportive procedures such as tightening, suspension, or canthal support may be combined with blepharoplasty. This helps maintain the correct lid position, protect the eye, and achieve a more harmonious aesthetic result.

Can I have both functional and cosmetic blepharoplasty?

Yes. Many patients have concerns that are both functional and aesthetic.

For example, a patient with heavy upper eyelids may have genuine visual obstruction, while also feeling that the eyes look tired or aged. In these cases, functional upper eyelid surgery can improve vision and enhance appearance.

Similarly, some patients may wish to combine functional upper eyelid surgery with cosmetic lower eyelid blepharoplasty to address under-eye bags, skin excess, or lower lid ageing. Where needed, lower lid reconstruction or support can be incorporated to improve both comfort and appearance.

The key is a careful assessment and an individualised surgical plan. Around the eyes, successful blepharoplasty is not simply about removing skin, muscle or fat – it is about addressing symptoms, balancing vision, eyelid support, symmetry, contour, and natural aesthetics.

Find out more

If you would like to know whether blepharoplasty is appropriate for you — whether for functional reasons, cosmetic improvement, or a combination of both – Mr Juling Ong can advise on the most suitable approach following a detailed consultation.

For more information or to arrange an appointment, please contact the clinic.

Abdominoplasty, or tummy tuck surgery, has long been popular among patients who have experienced significant weight loss, as it removes excess skin often left behind, creating a sleeker, smoother silhouette.

Plastic surgeons around the world have observed that patients who have undergone tummy tuck surgery often continue to lose weight in the months and years after surgery, but until recently, no official study had examined this phenomenon. Now, however, a group of surgeons from the Northwest University Feinberg School of Medicine in Chicago have done just that.

Weight loss carries on for up to five years after surgery

Dr John Y.S. Kim and colleagues assessed body weight changes in 188 patients – 97% of whom were women – for five years after abdominoplasty. The average pre-surgery weight of the patients was 168 pounds (76.2kg), and the average BMI was 27.7. The majority of patients who participated in the study underwent liposuction or a similar fat-reduction procedure at the same time as the abdominoplasty.

Follow-ups continued through to five years postoperatively, and the results are impressive:

  • At three to six months after surgery, the average weight loss was between three and five pounds (1.4 to 2.3kg), with a decrease in BMI of three per cent
  • Between one and four years, the average weight loss was around five pounds (2.3kg), with a BMI reduction of two per cent
  • By five years, average weight loss was nearly ten pounds (4.5kg), with BMI reduced by more than five per cent

In total, around 60% of patients studied continued to lose weight after surgery, showing a ‘near constant negative change in body weight that did not significantly change over time’, according to the study authors.

Why do patients continue to lose weight after a tummy tuck

A tummy tuck is a body-contouring procedure, not a weight-loss surgery. Excess skin and fat are removed, but this typically amounts to only a few pounds.

However, after surgery, patients continue to lose weight because they tend to develop healthy habits around nutrition and exercise. The study found that weight loss was greater in those with a higher BMI before surgery.

Since tummy tuck surgery removes excess skin and fat and can correct diastasis recti (abdominal muscle separation), patients often feel more mobile after their procedure. Physical activity is often easier and more enjoyable, which can encourage further weight loss.

Psychologically, a tummy tuck can help you feel better about your appearance, which can be a huge motivator to maintain or even improve upon your results.

While further research is still needed, another reason patients may be able to sustain weight loss after their tummy tuck is increased satiety. This means feeling fuller for a prolonged period after eating. According to a Plastic and Reconstructive Surgery study, three-fourths of participants reported greater satiety after their tummy tuck.

Researchers suggest this could be due to tightening of the abdominal muscles, which may restrict the stomach’s ability to expand, thus making it more difficult to overeat. Another possible reason is changes in the neuroendocrine system. Because hormones that stimulate hunger are stored in fat cells, tummy tuck surgery may reduce hunger by removing abdominal fat.

How does abdominoplasty work?

Abdominoplasty is an ideal procedure for someone who has lost significant weight, particularly in the abdominal region. It is also very popular with women who struggle to achieve a flat stomach after pregnancy and childbirth. It can be performed with or without liposuction to trim away excess, sagging skin on the belly and tighten the abdominal muscles, leaving you with a tauter, flatter midriff.

Mr Juling Ong offers three options for tummy tuck surgery:

  1. The full tummy tuck addresses the whole abdominal region, up to the ribs
  2. The mini tummy tuck deals only with the area beneath the belly button – often patients who are otherwise quite slim have a stubborn pouch in this area
  3. An extended tummy tuck involves a wider incision to take in the area of the ‘love handles’. This allows for more tissue to be removed and waist contouring to be performed

The size and position of the incision will depend on the type of abdominoplasty being performed, but Mr Ong is always careful to place it as low on the abdomen as possible, so that the scar can be easily hidden by clothing or swimwear.

If you would like to find out more about abdominoplasty, or book a consultation with Mr Ong, don’t hesitate to get in touch with us today.

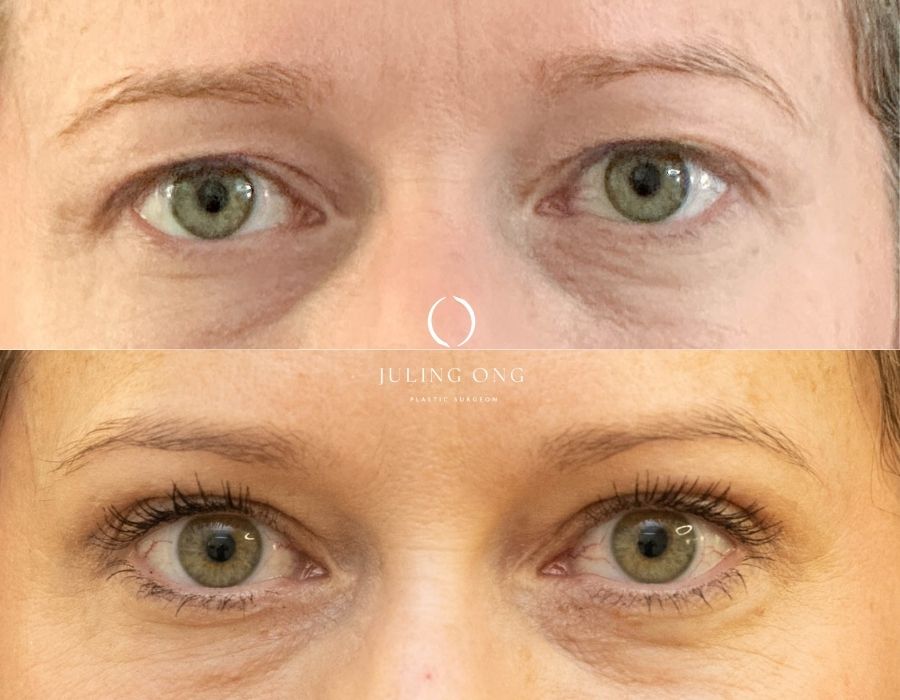
When patients look at upper eyelid before-and-after photos, the differences can seem subtle at first glance – yet the impact on eye openness, lash position, and overall freshness can be striking.

In this post, I’ll explain how I assess the upper eyelids and how I perform an upper blepharoplasty, also known as an upper eyelid lift.

The goal: brighter eyes that still look like you

Upper blepharoplasty is never about changing someone’s identity or creating an ‘overdone’ eyelid. I aim to:

  • Reduce heaviness from excess skin
  • Create a more youthful, fuller upper lid volume in the medial and lateral thirds
  • Restore a cleaner eyelid shape with a defined full-length eyelid crease
  • Improve eyelash position, curled upwards rather than downwards
  • Maintain a natural brow height, lid contour and balance
  • Where relevant, improve vision by removing skin that droops into the line of sight

What I assess before surgery

Every eyelid is different. A safe, natural result depends on diagnosing the cause of the eyelids looking heavy.

1) Brow position: the ‘frame’ above the eyelid

In many women, an attractive brow shape often has the outer (lateral) brow sitting just above the bony rim of the orbit. If the brow sits lower, it can push excess skin into the upper eyelid area, mimicking ‘lid excess’. When this occurs, removing skin from the lid may not improve its appearance.

In addition, brow shape matters: ideally, the brow has a gentle curve, with its highest point (the peak) around the junction between the inner two-thirds and the outer one-third—usually roughly in line with the outer corner of the eye (the lateral canthus).

Upper blepharoplasty surgery results

In this patient, the brow position has a small influence on eyelid heaviness – especially laterally. She wanted a natural brow, not a high ‘Botox brow’. As you can see, the brow is flat in the medial 2/3 and slopes gently downwards in the lateral third.

So in this case, I recommended Botox before surgery to:

  • gently lift the peak of the brow and stabilise the brow position in a natural, youthful position, which was the optimal aesthetic position for her
  • resist the brow dropping further after skin removal
  • ensure we were correcting the eyelid itself when the surrounding tissues are in the correct position

Some patients need a surgical brow lift instead; many like this patient don’t. The key is choosing the right procedure to help the patient achieve their individual goals.

2) Eyelid crease height (medial and lateral)

The eyelid crease is a major aesthetic landmark. I assess:

  • the height and shape of the crease
  • asymmetries
  • how much of the ‘tarsal platform’ (the visible eyelid skin below the crease) is showing

This helps plan incision placement and predict what changes will look natural.

3) Skin excess: aesthetic vs functional needs

I perform a pinch test with the patient:

  • Seated (maximum): shows the maximum amount of skin that could be removed cosmetically, and this is often done in the clinic as well as on the day of surgery.
  • Lying down (minimum): confirms how much skin can be removed safely, without significant compromise to eye closure or risk of excessive dryness.

A reliable indicator that the skin tension is ‘just right’ is a slight upward curl of the lashes at the end of surgery – without forcing the lid open and without creating a hollowed appearance. In practice, this is often between aesthetic and functional measures. The patient’s individual characteristics and pre-existing morbidities need to be considered when determining the amount of lagophthalmos (or gapping between the eyelids) that each patient can tolerate.

4) Eye health and lifestyle factors (this matters more than most people realise)

We discuss:

  • baseline dry eye symptoms
  • any eye conditions
  • vision
  • previous eye surgery
  • contact lens use
  • whether vision is obstructed by the lid skin (especially with reading or driving)
  • occupational factors (functional – such as driving, to cosmetic – such as client or public-facing jobs)

This guides how conservative we need to be and how we counsel patients in the peri-operative recovery.

The surgical plan: where the incisions go

Upper blepharoplasty incisions are planned to be hidden in the natural eyelid crease.

Upper blepharoplasty incisions

Lower incision: placed in the crease

In a typical Caucasian patient, the crease typically sits 6–10 mm above the lash line (this varies by anatomy and ethnicity). I measure this gently with the lid under light stretch and observe where the skin naturally folds when it moves. I can also confirm the tarsal height by flipping the lid over and measuring it with callipers. There is occasionally an asymmetry; if it is minimal, it can be accepted to preserve the natural skin crease.

Upper incision: determined by safe skin removal

This depends on the pinch test and brow-to-lid distance.

Medial and lateral limits (important for natural blending)

  • Medially: I generally limit the length of the incision to the region near the punctum (the inner corner tear drainage opening). If there’s a small amount of excess skin, also known as a ‘dog ear’, I will design a subtle extension angled upward and medially toward the glabella to remove this excess skin and achieve a smooth, flat medial contour.
  • Laterally: At the lateral canthus, I will angle the incision upwards along the line of a natural skin crease towards the lateral brow. This allows me to remove a bit more skin at this point, which helps to achieve a bit more tarsal platform show as well as curling the lashes up more in the lateral third.

This is one of the details that helps the eyelid look more beautiful, youthful and refined rather than ‘operated’.

What I do during the procedure (and why)

1) Skin excision: removing the excess skin drape without over-tightening

The most visible difference in ‘after’ photos is usually that:

  • the eyelid skin no longer folds onto the lashes
  • the eye lashes becomes more visible
  • the entire lid crease is visible from medial to lateral, which makes the eyes look more open and less tired

Ideally, skin removal also allows the lashes to roll slightly upwards, highlighting them against the paler skin of the upper eyelid.
From an aesthetic perspective, my goal is a smooth, natural fullness or convexity above the incision—especially laterally, which transitions to a flat or subtle concavity at the medial eyelid.

2) Muscle management: tailored, conservative

The eyelid muscle (orbicularis) contributes to:

  • eyelid fullness
  • blinking and eye closure

In selected patients, a small amount (up to 50%) of muscle can be removed to decrease heaviness. However, I’m cautious: removing too much can risk a weaker blink and dryness.

3) Fat: preserve what you need, remove what you don’t

The upper eyelid contains fat pads, which are really important in the overall shape of the upper eyelid.

Medial fat pad (inner corner fullness)

This is often the part patients describe as a ‘puffy inner corner’. If it’s prominent and causing a discrete focal bulge medially, I will remove a small amount – carefully – as it is close to the superior oblique muscle, which helps move the eye. It can also be mobilised or transposed to the medial third of the eye to help address excessive hollowing, a feature of ageing. This intra-orbital fat pad often becomes more prominent with ageing.

A key principle: the medial area should look smooth and flat, not hollow and not bulging. If there is excess skin medial to the punctum, I may remove skin there after addressing the medial fat, so the inner contour remains natural. This bulge is addressed primarily by fat removal, but may also require skin removal if it remains lax and excessive.

Central pre-aponeurotic fat (the ‘supporting fullness’)

This central fat often helps keep the eyelid looking youthful. I generally prefer to preserve it, and in some patients, I gently mobilise it from lateral to medial to soften a central hollow or to treat or prevent the classic “A-frame” hollowing. This fat pad often atrophies with age, resulting in a hollow appearance to the eye socket and upper lid.

Lacrimal gland (outer upper lid fullness)

Sometimes, the lacrimal gland (tear gland) can slip down from its position behind the orbital rim and project into the eyelid or appear prominent. This can:

  • add bulk to the outer third of the lid
  • reduce visible crease definition
  • reduce the visible ‘tarsal platform’ (that clean lid space people often want)

If this is contributing, it needs to be recognised and managed appropriately – otherwise, a simple skin excision won’t fully address lateral heaviness. In my practice, I usually reposition this under the lateral orbital bone with a couple of tiny sutures

4) Brow fat suspension sutures (when appropriate)

In many patients, I will use supportive sutures to:

  • improve the subbrow contour in the lateral third of the eye
  • increase visibility of the tarsal platform
  • define the transition between brow and lid

This can subtly improve the ‘frame’ of the eye without changing the patient into a different person.

So what changes in the ‘after’ photo?

In my patient, the typical visible differences are:

  • The upper lid skin no longer rests on the lashes
  • A cleaner, full-length eyelid crease
  • More visible tarsal platform of about 2mm (without overexposure)
  • A smoother inner corner (less medial puffiness)
  • A gentle lateral lift in the eyelash angle and slightly wider tarsal platform
  • A brow that looks stable and natural, not artificially high
  • The impression of a slightly more upturned lateral canthus is created by removing the overhanging fold of skin from the upper lid
  • A fresher, more youthful appearance with the eyes still looking unmistakably like her
  • A super, natural appearance without any visible signs of surgery, even on close inspection

What patients usually ask next

Will it look natural? That’s my goal. The operation should make you look rested, not ‘done’.

Is it just skin removal? Not always. Skin is part of it, but brow position, incision placement, skin and muscle resection, fat distribution, and lacrimal gland position often matter just as much.

Will it help vision? If skin is encroaching on your visual field, it often does. We can discuss this during the assessment.

If you’re considering upper blepharoplasty

A good consultation is half the operation. The safest and most natural results come from careful assessment, conservative planning, and an approach that preserves youthful structure while removing what’s truly excessive.

To book a consultation with Mr Juling Ong, call 020 7927 6528 or email info@julingong.com.

In recent years, the global rise of K-pop, Korean drama, Japanese fashion, and Southeast Asian influencers has ignited worldwide interest in Asian beauty standards. Yet while social media, music and entertainment have drawn more attention to the Asian aesthetic, the truth is far more nuanced: there is no single ‘Asian’ look. Asia is the largest and most diverse continent in the world – stretching from the Middle East to Japan, from Siberia to Sri Lanka – and its range of ethnicities, facial structures and beauty ideals is vast.

Today, modern life has made this picture even more multifaceted. Increasing numbers of people, especially in cosmopolitan cities like London, São Paolo, Toronto, Singapore, and New York, are of mixed Asian and non-Asian heritage. Their facial features reflect the blending of multiple ancestries – combinations that can be incredibly beautiful yet incredibly unique.

Understanding this diversity is essential for anyone seeking cosmetic surgery, particularly facial surgery, where subtle differences in anatomy determine what is both possible and natural. As a consultant craniofacial and facial aesthetic surgeon of mixed Asian and Western heritage, Mr Juling Ong brings a deeply personal understanding of these variations. His own experience of blended ethnicity, combined with advanced surgical training, enables him to appreciate the broad spectrum of facial forms that exist across Asia and beyond — and to tailor each treatment with cultural sensitivity and anatomical precision.

This blog explores the complexity and beauty of Asian aesthetic goals, the importance of understanding mixed-heritage anatomy, and why personalised, respectful surgical planning is the cornerstone of excellent results.

Asia is not a single aesthetic category

When people refer to ‘Asian features’, they often unknowingly compress the appearances of over 4 billion people into one stereotype. In reality, the continent’s diversity is extraordinary, and although there may be some regional traits, there will always be significant variation even within the regions of Asia described below.

East Asia (China, Korea, Japan)

Common traits may include:

  • Smooth, wide facial contours
  • Thicker eyelid skin
  • Lower nasal bridges
  • Softer nasal cartilages

Aesthetic preferences often include soft, refined features and balanced proportions.

Southeast Asia (Malaysia, Singapore, Thailand, Vietnam, Indonesia, Philippines)

Features can vary considerably due to the significant population mixing in this region but often include:

  • Wider or shorter midfaces
  • Thicker skin
  • Rounder facial outlines

Here, aesthetic goals often focus on facial slimming, midface refinement and gentle nasal augmentation.

South Asia (India, Pakistan, Bangladesh, Sri Lanka)

Common features may include:

  • Higher nasal bridges
  • Sharper angles
  • High variation in skin thickness

Patients often seek refinement rather than augmentation.

Central, West Asia and the Middle East

These populations often present with:

  • Stronger bony structures
  • High nasal dorsum
  • Defined profiles

Adjustments often involve softening rather than adding projection.

These categories alone highlight one key truth; there is no single ‘Asian’ beauty ideal – only a collection of regional and cultural aesthetics with significant intraregional variation.

The modern landscape: the beauty of mixed heritage

The last several decades have brought unprecedented multiculturalism. As societies have become more interconnected, mixed-heritage families are increasingly common, leading to spectacular and diverse combinations of facial features.

A patient may have:

  • Chinese and Caucasian ancestry
  • Korean and Filipino heritage
  • Indian and Malay parentage
  • Japanese and African heritage
  • Or, like Mr Ong himself – a blend of Asian and Western backgrounds that produces a unique facial form

Mixed-heritage patients often present with a fusion of characteristics from each ancestral group. For example, someone of East Asian and Caucasian heritage might have:

  • A higher nasal bridge than many Asian patients, but softer cartilage than many Western patients
  • Thinner eyelid skin, but an incomplete or asymmetric eyelid crease
  • A narrower jawline paired with a fuller midface

These combinations cannot be approached with a ‘textbook’ surgical plan. They require a surgeon who:

  • Understands the nuances of each contributing ethnicity
  • Can anticipate how different tissues behave
  • Recognises how beauty ideals vary between cultures
  • Appreciates the emotional significance of preserving identity
  • Has personal or professional experience navigating multiple cultural worlds

Mr Juling Ong London Paediatric Plastic SurgeonThis is what makes Mr Juling Ong’s perspective – as a surgeon of mixed Asian heritage – both rare and invaluable.

He understands the desire to refine certain features without losing what makes a person uniquely themselves. Mixed-heritage patients are not seeking to choose one side of their identity over the other – they want harmony and balance that honours their full story.

Why cultural sensitivity matters in cosmetic surgery

In many Asian cultures, subtlety is the guiding aesthetic principle. Changes should look natural, harmonious and effortless. The aim is often to look:

  • More awake
  • More refined
  • More balanced
  • More harmonious with one’s own facial structure, not dramatically transformed

This stands in contrast to some Western aesthetic trends that favour more sculpted, high-impact enhancement (fuller lips, pronounced cheekbones, strong jawlines). While neither approach is ‘right’ or ‘wrong’, it illustrates that different cultures value different forms of beauty.

Understanding these differences is essential. A surgeon must listen closely and must avoid imposing Western ideals onto Asian or mixed-Asian patients.

A deeply personal approach to common procedures

Several facial procedures are especially popular among Asian and mixed-heritage patients. When performed with cultural awareness and anatomical insight, they produce beautiful, natural results.

1. Asian blepharoplasty (double eyelid surgery)

The creation of a double eyelid crease is one of the most commonly requested procedures among East and Southeast Asian patients. Importantly, the aim is not to create a Western eyelid, but to enhance the natural almond eye shape. Mixed-heritage patients may have:

  • A partial crease
  • Asymmetrical creases
  • A higher crease on one eye
  • A thicker or thinner eyelid skin fold

Surgery must be customised accordingly.

Key goals include:

  • Enhancing expressiveness
  • Creating a crease that suits the underlying anatomy
  • Ensuring the eyelid remains ethnically harmonious
  • Avoiding an overly high crease

Understanding variations in crease position and fat distribution is essential, especially when features from two or more ethnic backgrounds are present.

2. Facial sculpting: cheekbone and jawline refinement

While Western societies often celebrate strong cheekbones and angular jawlines, many Asian cultures prefer:

  • Softer contours
  • Slimmer lower faces
  • A gentle V-line silhouette

Procedures such as cheekbone reduction (zygomatic remodelling) and jawline contouring (mandibular reduction) are common when patients desire a more delicate facial outline.

Mixed-heritage patients often present with hybrid features such as:

  • Stronger bone structure from one side of the family
  • Softer contours from the other
  • Asymmetries that reflect differences between ancestral groups

These nuances must be respected. The aim is to enhance facial harmony — not to homogenise features.

3. Asian rhinoplasty

Asian rhinoplasty is another area where individualised planning is essential. Asian noses often feature:

  • Lower bridges
  • Softer cartilage
  • Thicker skin
  • Wider alar bases

But in mixed-heritage patients, the nasal form may blend characteristics in unexpected ways. Some may have:

  • A high dorsum but weak tip
  • A strong tip but a flat radix
  • Narrow nostrils but thick alar skin

These combinations require thoughtful modification of standard techniques. The goal is always:

  • Elegant definition
  • Harmony with the eyes and midface
  • Respect for ethnic identity
  • Long-term structural support

Not overprojection or Westernisation.

The emotional importance of identity

Perhaps the most important aspect of Asian and mixed-heritage aesthetic surgery is the emotional dimension.

Patients often seek enhancement that:

  • Leaves their cultural identity intact
  • Respects their ancestry
  • Feels authentic to who they are
  • Enhances confidence without changing their fundamental appearance

This requires trust — and a surgeon who listens deeply, asks the right questions, and understands that identity cannot be altered surgically, only expressed more confidently.

Why a thorough consultation matters

Mr Ong always conducts a full, detailed consultation that covers:

  • The patient’s aesthetic goals
  • Their ethnic background and heritage
  • Anatomical variation
  • Cultural expectations
  • Personal preferences
  • Long-term hopes
  • Structural limitations and possibilities

This ensures every treatment is customised, respectful and safe.

For mixed-heritage patients, this conversation is especially valuable. Discussing the blend of features informs a more thoughtful surgical plan — one that acknowledges the beauty of their individuality.

Conclusion: celebrating diversity, tailoring with precision

Asian beauty — in all its forms — is incredibly diverse. And in today’s interconnected world, mixed-heritage patients represent an increasingly important and beautiful expansion of that diversity.

Cosmetic surgery for Asian and mixed-Asian patients is not about imposing uniform ideals. It is about understanding:

  • Cultural nuance
  • Anatomical variation
  • Personal identity
  • Regional beauty values
  • The emotional significance of subtle refinement

The best results are those that preserve authenticity, enhance natural features, and honour the unique blend of ancestry that makes each patient who they are.

For those seeking facial cosmetic surgery, choosing a surgeon who understands this — through training, experience, and often lived cultural reality — is essential.

If you would like to learn more or discuss your goals in person, please contact:
📞 020 7927 6528
📧 info@julingong.com

Mr Juling Ong has recently spent five days representing the Great Ormond Street Craniofacial Team and spoke on Machine Learning at the 21st Congress of the International Society of Craniofacial Surgery in Shanghai, China.

Mr Juling Ong attended the Head and Neck Reconstruction Workshop in South Korea

Mr Juling Ong at the podium lecturing on research in machine learning for craniosynostosis, Mr Juling Ong and Professor JW Choi at the Asan Medical Centre, Seoul, Mr Juling Ong and Dr JL Park at the 345 Plastic Surgery Clinic, Seoul (clockwise from top left).

He then went to Seoul to visit a friend and colleague Professor JW Choi at the Asan Medical Centre. During his visit to South Korea, he attended the Head and Neck Reconstruction Workshop as well as the Korean Society for Simulation in Surgery Symposium.

Plastic surgery costs are always a factor in the decision-making process. These costs can vary widely, not only in London but throughout the UK, and it can seem tempting to go for the cheaper option. However, it is essential to remember that when it comes to your body, face or breasts, safety should be your top priority.

When you book a procedure with a top plastic surgeon, some of what you are paying for is the security of knowing your surgeon has a wealth of training and experience behind him.

But what else goes into the cost of plastic surgery? We have broken it down to help you understand exactly what it is you are paying for.

Costs applicable to all procedures

Although there are some pricing differences between different plastic surgery procedures (more on that below), some costs apply to whatever surgery you choose. Here’s a breakdown of what you are paying for and why:

The surgeon’s fee:

Like all professionals, plastic surgeons charge a fee for their service, and the amount they charge will reflect their expertise, training and experience, as well as the complexity of the operation they are performing.

The anaesthetist’s fee:

Contrary to popular belief, the anaesthetist doesn’t just administer your anaesthetic prior to the procedure but is responsible for monitoring all your vital statistics during so the surgeon can concentrate on the operation. If you have a general anaesthetic, the anaesthetist will also wait to check that you are well when you come around, ensuring you wake up with minimal nausea and pain. All of this incurs a fee for the anaesthetist’s time and expertise.

Theatre fees:

When a surgeon operates out of a private hospital, they pay a fee to use the operating theatre and equipment, which is reflected in the cost of the procedure. Mr Juling Ong operates out of leading London private hospitals which offer state-of-the-art facilities and outstanding patient care.

Hospital stay:

Some procedures will require an overnight stay in hospital, and this will also be included in the price.

Post-op medication, etc:

You may well be prescribed some medication to take after the operation to help with any bruising, swelling or pain. Some procedures will require you to wear a compression garment. All of this may be included in the cost of your surgery.

Price variants between procedures

Why do some plastic surgery procedures cost more than others? There are several factors at play, but some of the main considerations are:

  • Duration: some procedures take longer than others or you may have combined procedures. This means there is more to pay in terms of the fee to use the operating theatre and equipment, plus the cost of paying the anaesthetist, surgical team and the surgeon.
  • Implants: while some procedures, such as rhinoplasty (nose job) or abdominoplasty (tummy tuck) require reshaping or removing existing structures, others, like breast augmentation, require the insertion of an implant, and the price of surgery will include the cost of the implant itself. The type of implant used may also affect the price. Mr Juling Ong only uses the highest-quality implants made from materials with a proven track record of safety in clinical use.
  • Anatomical differences: while unusual, it is possible that some patients may be charged a slightly higher fee than others because of certain anatomical features which make surgery more complicated.

Why not go abroad?

It is true that some ‘cosmetic surgery holiday’ providers offer prices that are difficult for UK surgeons to beat. However, tread very carefully when booking surgery abroad.

Mr Juling Ong is a member of the British Association of Aesthetic Plastic Surgeons (BAAPS) and they have previously warned of the mounting cost of cosmetic surgery tourism, both to the NHS in the form of revision surgery and the patient.

In a survey they conducted, 83% of respondents cited lower costs as the primary reason for choosing surgery abroad. However, alarmingly, 66% of respondents stated they would not make the same decision and nearly half expressing regret.

Planning plastic surgery?

Some things to consider are:

Surgeon qualifications

Surgical qualifications vary widely between countries, so while the letters behind someone’s name might look very impressive, it is important to find out what they mean. In the UK, surgeons are required to have reached Consultant level (which means a minimum of six years’ specialist training, as well as passing several rigorous examinations) before they can offer private plastic surgery.

Regulation

Plastic surgery in the UK is heavily regulated by the Healthcare Commission and the General Medical Council, which typically makes it more expensive for surgeons, hospitals and clinics than abroad. Here, plastic surgeons must also have extensive malpractice indemnity in the rare event that something goes wrong. But this does ensure that you are fully protected and receive the best possible care and treatment.

Communication

One of the most essential things when choosing your plastic surgeon is whether you feel you can understand each other – does s/he understand the result you are hoping for? Do you understand the pre- and post-op advice s/he is giving you?

Follow-up treatment

Even if the surgery goes smoothly, you will require follow-up appointments to check on your progress, and if there are complicationsThe regulations may not be the same in the country you choose for your surgery, so it is important to be aware of that before signing anything.

For more information on our plastic surgery pricing, call 020 7927 6528 or email info@julingong.com to speak to Mr Ong’s team.